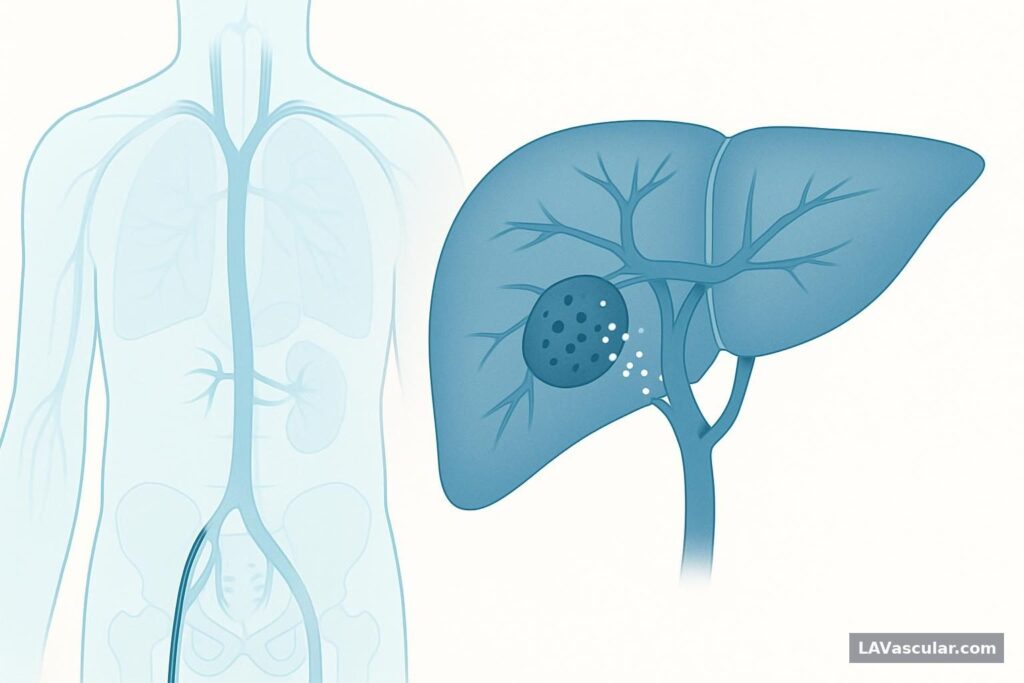
Chemoembolization is a minimally invasive, targeted treatment that delivers chemotherapy into the arteries feeding a liver tumor and then blocks part of that blood supply. It is most often used for hepatocellular carcinoma and selected liver-dominant metastases, including tumors that began as colorectal cancer.
The most common form is transarterial chemoembolization (TACE). An interventional radiologist uses imaging and a small catheter to treat the tumor while limiting chemotherapy exposure to the rest of the body.
What is chemoembolization?
Chemoembolization combines two treatments: chemotherapy and embolization. Chemotherapy is delivered directly into or near the tumor blood supply, and embolic material is then used to slow or block blood flow to the tumor.
Liver tumors often receive much of their blood supply from the hepatic artery, while most healthy liver tissue is supplied mainly by the portal vein. This difference can allow a physician to selectively target the arteries that feed a tumor.
How does chemoembolization work?
During chemoembolization, an interventional radiologist guides a catheter into branches of the hepatic artery that supply the tumor. Chemotherapy and embolic agents, such as small particles or drug-eluting beads, are delivered through the catheter.
- The chemotherapy is concentrated near the tumor.
- The embolic material reduces blood flow to the tumor.
- Reduced blood flow can deprive tumor cells of oxygen and nutrients.
- Blocking blood flow may help keep the chemotherapy in contact with the tumor longer.
The intended result is tumor cell injury or death, tumor shrinkage, or slower tumor growth. The exact technique, chemotherapy agent, and embolic material depend on the tumor type, liver function, arterial anatomy, and treatment goals.
Who needs chemoembolization for liver cancer?
Chemoembolization may be considered for people with liver tumors that cannot be safely removed with surgery or treated adequately with another local therapy. A multidisciplinary liver cancer team usually reviews imaging, liver function, symptoms, tumor burden, and overall health before recommending treatment.
Common reasons to consider chemoembolization include:
- Unresectable primary liver cancer, especially hepatocellular carcinoma.
- Liver-dominant metastatic disease from another cancer, such as colorectal cancer.
- Patients who are not candidates for surgery, liver transplantation, or local ablation.
- Bridge therapy before liver transplantation to help control tumor growth while a patient awaits transplant.
- Downstaging selected tumors so that surgery, transplantation, ablation, or another treatment may become possible.
- Palliative treatment to control tumor-related symptoms and support quality of life when cure is not possible.
Who may not be a candidate for chemoembolization?
Chemoembolization is not appropriate for every liver tumor. Severe liver dysfunction, a very poor performance status, extensive tumor involvement of the liver, certain patterns of portal vein blockage, active infection, significant kidney dysfunction, or an unsafe arterial pathway may change the risk-benefit balance.
The care team also considers contrast allergy, blood counts, clotting status, biliary obstruction, prior liver treatments, and whether the tumor has spread outside the liver. Some patients may be better served by systemic medication, surgery, radiation therapy, transplantation, ablation, or another catheter-based liver treatment.
How is chemoembolization performed?
Chemoembolization is usually performed by an interventional radiologist in an angiography suite or hospital procedure room. It is commonly done with local anesthesia at the access site and conscious or moderate sedation; some patients need deeper anesthesia depending on their condition and the planned treatment.
What happens before chemoembolization?
Before treatment, the team reviews liver imaging, usually CT or MRI, to map the tumor and assess liver anatomy. Blood tests commonly check liver function, kidney function, blood counts, and clotting.
Some patients undergo a planning angiogram before treatment. This maps the liver arteries and helps identify vessels that could carry treatment material outside the liver, such as toward the stomach or intestine.
What are the steps of chemoembolization?
- The skin over an artery is cleaned and numbed. The common access site is the femoral artery in the groin, although the radial artery at the wrist may be used in selected patients.
- A small needle puncture is made, and a thin catheter is placed into the artery.
- Using fluoroscopy, or real-time X-ray guidance, the interventional radiologist advances the catheter through the arterial system to the hepatic artery and then into the branch or branches supplying the tumor.
- Contrast dye is injected to confirm blood flow and identify the tumor-feeding vessels.
- A combination of chemotherapy and embolic agents, such as small particles or beads, is delivered directly into the tumor blood supply.
- The catheter is removed, and pressure or an artery-closing device is used at the access site.
The procedure often takes about one to several hours, depending on the number, size, location, and blood supply of the tumors. Treatment may be performed in stages when disease involves more than one area of the liver.
What is recovery like after chemoembolization?
Most patients are observed in the hospital after chemoembolization, often overnight, although the required stay depends on the extent of treatment, symptoms, liver function, and other medical conditions. The care team monitors pain, nausea, fever, blood pressure, access-site bleeding, and liver function.
What is post-embolization syndrome?
Post-embolization syndrome is a common group of temporary symptoms caused by tumor ischemia and inflammation after embolization. It can include abdominal pain, fatigue, low-grade fever, nausea, vomiting, and reduced appetite.
Symptoms are usually managed with pain medication, anti-nausea medication, hydration, and rest. Patients should contact their care team promptly for severe or worsening pain, persistent high fever, uncontrolled vomiting, jaundice, confusion, bleeding, chest pain, shortness of breath, or signs of infection.
When can patients return to normal activities?
Many people need several days to recover from fatigue, pain, and nausea, and some need longer depending on the amount of liver treated and their baseline health. The treating team provides individualized instructions about bathing, lifting, driving, medications, diet, work, and follow-up.
Follow-up CT or MRI is commonly used to assess whether the treated tumor has lost blood supply, shrunk, or remains active. Additional chemoembolization or another treatment may be recommended if there is residual or recurrent tumor.
What are the benefits and expected outcomes of chemoembolization?
Chemoembolization can control tumors in the liver, delay growth, relieve symptoms, and help preserve treatment options for selected patients. In unresectable hepatocellular carcinoma, it can improve tumor response and survival compared with systemic chemotherapy alone in appropriately selected patients.
Potential benefits include:
- Tumor shrinkage or delayed tumor growth.
- Control of liver-dominant cancer when surgery is not possible.
- Possible downstaging to make surgery, transplantation, ablation, or another local treatment feasible.
- Bridge treatment to help control tumors before liver transplantation.
- Symptom relief and support for quality of life in advanced liver cancer.
- Less whole-body chemotherapy exposure than standard systemic chemotherapy because treatment is delivered through tumor-feeding arteries.
Results vary substantially. Important factors include the tumor type, number, size, location, arterial blood supply, degree of liver involvement, portal vein flow, liver function, prior treatments, spread outside the liver, and a patient’s overall health.
Chemoembolization is often one part of a broader cancer plan. Depending on the situation, it may be used with surgery, liver transplantation, systemic therapies such as targeted therapy or immunotherapy, radiation therapy, or thermal ablation.
What are the risks of chemoembolization?
Chemoembolization is generally less invasive than open surgery, but it has meaningful risks. The risk level depends on liver reserve, tumor extent, arterial anatomy, kidney function, and the amount of liver being treated.
Possible risks and side effects include:
- Post-embolization syndrome: pain, fever, nausea, vomiting, fatigue, and loss of appetite.
- Bleeding, bruising, infection, blood clot, or artery injury at the groin or wrist access site.
- Allergic reaction or kidney injury related to contrast dye.
- Temporary or, less commonly, serious worsening of liver function.
- Liver infection or abscess, particularly in patients with certain prior bile duct procedures or altered biliary anatomy.
- Unintended embolization or chemotherapy delivery to nearby organs or normal liver tissue, which can injure surrounding tissue.
- Ulceration or inflammation of the stomach, intestine, gallbladder, pancreas, or skin if treatment material reaches non-target arteries.
- Rare serious complications, including liver failure or death.
An interventional radiologist and oncologist should review the expected benefits, alternatives, and risks for the individual patient. Patients should also make sure the team knows about all medications, especially blood thinners, diabetes medications, allergies, kidney disease, prior biliary surgery, and prior liver treatment.
Chemoembolization vs Y-90 radioembolization vs liver tumor ablation
Chemoembolization, radioembolization, and ablation are different local treatments for liver tumors. The best option depends on the cancer type, size and number of tumors, location, liver function, blood vessels, prior treatment, and whether the goal is cure, transplant bridging, downstaging, or disease control.
Chemoembolization vs Y-90 radioembolization
Chemoembolization uses chemotherapy plus arterial embolization. Y-90 radioembolization (SIRT) delivers microscopic radioactive beads through the liver arteries to provide internal radiation to tumors.
Both treatments are catheter-based and use imaging guidance, but they work differently and have different planning requirements and side-effect profiles. Y-90 may be considered in situations where embolization alone is less suitable, including selected cases involving portal vein thrombosis, but candidacy must be determined individually.
Chemoembolization vs liver tumor ablation
Liver tumor ablation destroys a tumor directly using a needle-like probe and heat from microwave or radiofrequency energy. It is often most useful for a limited number of relatively small tumors that can be safely reached without injuring critical structures.
Chemoembolization treats tumors through their arterial supply and can be useful when there are multiple tumors or when direct needle access is difficult. In some cases, ablation and chemoembolization are combined to improve local tumor control.
Where does portal vein embolization fit?
Portal vein embolization is not a liver cancer treatment that directly kills a tumor. It is a preoperative procedure that redirects portal blood flow so the planned remaining liver can grow before major liver surgery.
For patients being considered for liver resection, portal vein embolization may help make surgery safer by increasing the future liver remnant. It is evaluated separately from chemoembolization and may be part of a surgical treatment plan.
Frequently Asked Questions
How much does chemoembolization cost?
The cost varies by hospital, insurance plan, medications used, imaging, anesthesia or sedation needs, and whether an overnight stay is required. Ask the hospital financial counselor and your insurer for an estimate of covered and out-of-pocket costs before treatment.
Is chemoembolization painful?
The access site is numbed, and sedation is usually used, so most patients do not feel sharp pain during catheter placement. Abdominal discomfort can occur during or after treatment, and pain medication is provided as needed.
How long does it take to recover from chemoembolization?
Many patients stay in the hospital overnight and need several days to recover from fatigue, nausea, fever, or abdominal pain. Recovery can take longer after treatment of a large portion of the liver or in people with reduced liver function.
What is the success rate of chemoembolization for liver cancer?
There is no single success rate because results depend on cancer type, tumor size and number, liver function, blood flow, and treatment goals. Chemoembolization can shrink or control selected liver tumors, delay growth, and help bridge or downstage some patients for other treatments.
What are the risks of chemoembolization?
Common short-term effects include pain, fever, nausea, fatigue, and appetite loss, often called post-embolization syndrome. Less common but serious risks include infection, bleeding, liver injury or failure, kidney injury, and unintended treatment of nearby organs.
Chemoembolization vs Y-90: which is better?
Neither treatment is best for every patient. Chemoembolization uses chemotherapy and embolization, while Y-90 uses internal radiation; the appropriate choice depends on tumor characteristics, liver function, portal vein flow, anatomy, and overall treatment goals.
Does insurance cover chemoembolization?
Many insurance plans, including Medicare in appropriate circumstances, may cover medically necessary chemoembolization for liver tumors. Coverage, prior authorization requirements, and patient cost-sharing vary, so confirm details with your insurer and treatment center.
How long does chemoembolization last?
The effect on a treated tumor varies, and follow-up CT or MRI is needed to determine the response. Some patients need repeat chemoembolization or additional therapies if tumor remains active or grows elsewhere in the liver.
Frequently Asked Questions
What is chemoembolization and how does it work?
Who is a candidate for chemoembolization?
What happens during a chemoembolization procedure?
What are the benefits of chemoembolization for liver cancer?
Are there any risks associated with chemoembolization?
Can chemoembolization be combined with other cancer treatments?
How does chemoembolization differ from systemic chemotherapy?
What should patients expect in terms of recovery after chemoembolization?
Minimally invasive treatment options for liver cancer (hepatocellular carcinoma and liver metastases)
Portal Vein Embolization
Devices: Embolic beads, Coils
Other treatment options
- Surgical resection
- Liver transplant
- Systemic therapy (immunotherapy, targeted drugs)
- Radiation therapy (SBRT)